Tag: Prenatal Care

  • Signs Of Pregnancy

    Pregnancy & Prenatal Care

    What to Look For

    Do you think you might be pregnant? Here are some signs to look for:

    *  You have missed a menstrual period. You are at least 2 weeks late. {Note: Stress or illness can cause your period to be late, too. And, some women do not have regular periods. It may be hard for them to know if their period is  2 weeks late. Other women can have a light menstrual period or spotting and still be pregnant. So watch for other signs also listed here.}

    *  You feel tired. This is the most common sign.

    *  You feel sick to your stomach. You may even throw up. This is called “morning sickness.” But it can occur any time of day or night.

    *  You need to pass urine more often.

    *  You have food cravings.

    *  Your taste for certain foods changes.

    *  You have a metallic taste in your mouth.

    *  There are changes in your breasts.

    – They feel tender.

    – They feel tingly.

    – They are swollen.

    – The dark areas around your nipples are darker than before.

    – The tiny glands around your nipples stick up.

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Backaches

    Pregnancy & Prenatal Care

    Causes

    Pregnant women get backaches because:

    *  The growing uterus and extra weight pull the body forward. Standing this way can strain the back muscles.

    *  Hormones are released during pregnancy. These make the ligaments soften and stretch. Ligaments are tissues that surround and support the joints.

    *  Joints in the lower back get sore from pressure. This happens to joints in the pelvic area, too. The baby is growing in size and weight.

    *  The baby presses against the tailbone.

    Prevention

    Do exercises your health care provider tells you to do. Use good posture, too. Keep your spine straight when you are standing. Have a friend check your back for curving: Stand with your heels against a wall. Ask your friend to look at your back. Tell him or her to let you know if it curves. Center your weight over the pelvic area. Be careful when you bend over, too. Bending wrong can give you a backache.

    Back Labor

    Most women have some back pain during labor. Some women have it through their whole labor. This is called back labor. It is caused by the way the baby is lying. The back of the baby’s head presses against the tailbone. Or it may press slightly to one side of it. Back labor can occur in preterm labor, too.

    Questions to Ask

    Self-Care

    Tips for Good Posture

    When you stand:

    *  Stand straight.

    *  Tuck in your bottom.

    *  Don’t hollow your back.

    *  Don’t tighten your shoulders or hold them back. Keep them dropped.

    *  If you have to stand for a long time: Stretch your feet and shift your weight. Rest one foot and then the other on a footstool or telephone book.

    When you sit:

    *  Sit on a straight chair with a high back.

    *  Rest your back against the chair’s back.

    *  Put a pillow at the small of your back.

    *  Rest one or both feet on a footstool.

    *  Don’t sit too long. It strains your lower back. Get up and walk around.

    When you bend:

    *  To pick something up, squat down on your heels and bend your knees. Keep your upper body straight. Don’t lean over from the waist. Use the strength from your legs, not your back.

    *  To do something down low, kneel or squat. Or get down on all fours. That way, you help take the baby’s weight off your spine.

    When you lie down or sleep:

    *  Use a firm mattress. If you don’t have one, have someone help you place a board under your mattress. Or have someone put your mattress on the floor.

    *  Lie on your left side with your knees bent. Bend the upper knee more than the lower knee. Leave a lot of space between your legs.

    *  Put a pillow under your upper knee and leg.

    Other Self-Care Tips

    *  Don’t gain too much weight.

    *  Wear shoes with low (but not flat) heels.

    *  On a long car ride, stop every two hours. Get out and walk around.

    *  Don’t take medicine for pain. Ask your health care provider first.

    *  Don’t lift objects over 15 pounds.

    *  Don’t do exercises where you lift both legs at the same time.

    *  Do exercises for stronger back and belly muscles. Ask your health care provider for these.

    *  Do relaxation and deep breathing exercises. Do yoga.

    *  Have someone massage your lower back. Massage won’t cure a backache. It can loosen tight muscles, though.

    *  Apply warm, moist heat to your back. Use a hot water bottle or warm wash cloth.

    *  Ask your health care provider if you should wear a back support girdle, a back brace, or a special elastic sling.

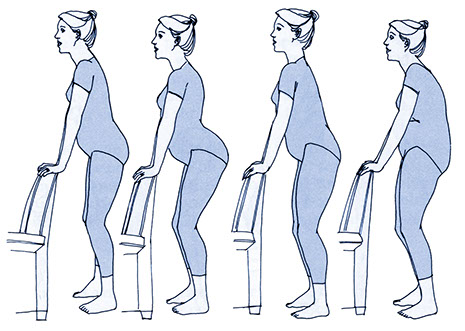
    *  Do an exercise called the “pelvic rock”. This exercise helps your lower back be more flexible. It helps make the muscles in your belly stronger.

    You can stand to do the pelvic rock.

    Step 1

    *  Stand 2 feet away from the back of a chair.

    *  Put your hands on the chair’s back. Keep your elbows straight.

    *  Bend a little forward from your hips.

    Step 2

    *  Push your hips backward and relax the muscles in your belly. Relax your back.

    *  Bend your knees a little.

    Step 3

    *  Slowly pull your hips forward.

    *  Tuck your buttocks under as if someone were pushing you from behind.

    Step 4

    *  Repeat steps 1, 2, and 3.

    Illustration of pregnant women doing the pelvic rock exercise while standing.

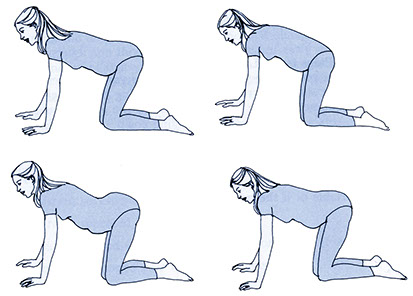
    You can do the pelvic rock on your hands and knees.

    Step 1

    Get down on all fours. Have your knees slightly apart. Have your back and elbows straight.

    Step 2

    Breathe in. As you breathe in, relax your back. Use the muscles in your lower belly.

    Step 3

    Breathe out. As you breath out, let your back relax down to a flat position. Do not let your back sag.

    Step 4

    Repeat steps 1, 2, and 3.

    {Note: Tell your health care provider if you get pain when you do the pelvic rock. Ask for help if you have a problem doing the pelvic rock.}

    Illustration of pregnant women doing the pelvic rock on hands and knees.
    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Bleeding

    Pregnancy & Prenatal Care

    Pregnant women sometimes have light spotting. That’s when a tiny bit of blood leaks from the vagina or the surface of the cervix. It may happen after a vaginal exam. It may also happen after sex. If the blood starts out pink or red and turns dark brown, it is not active bleeding. This is not usually a problem. But let your health care provider know when there is any bleeding. He or she will decide what to do. Bleeding can be a sign of a problem if:

    *  The blood is bright red.

    *  Pain or cramps are present, too.

    *  The bleeding is heavy. Heavy means the bleeding soaks a sanitary pad.

    *  The spotting keeps going on.

    Causes

    Before the 20th week, bleeding could be, but is not always, a sign of miscarriage. Other causes of bleeding include:

    *  Loss of the mucus plug

    *  Kidney infection

    *  Preterm labor

    *  Placenta previa and other problems called vasa previa and marginal previa

    *  Placenta abruptio

    *  Swollen cervix

    Placenta Previa

    The placenta carries oxygen and food to the baby. In most pregnancies, the placenta attaches high in the uterus. In placenta previa, it attaches low, over the cervix. The lower uterus stretches during late pregnancy. Parts of the placenta tear from the wall. That causes bleeding.

    Placenta previa is rare. It happens in only 1 in 200 pregnancies. Its cause is not known. Falls and injuries are not factors. Symptoms of placenta previa are:

    *  Bright red vaginal bleeding. This could start as early as the 24th week. Often, it starts during the 34th or 35th week.

    *  Usually, there is no pain or cramping.

    A woman may not know that she has placenta previa until bleeding happens. Then an ultrasound test can show the problem.

    Women with placenta previa have to spend a lot of time in bed. Bed rest may last late into the pregnancy. Bed rest gives the baby time to grow. It prevents stress to the uterus. The goal is to keep blood loss down. A lot of blood loss means danger for both mother and baby. In severe cases, the mother may have to go to the hospital for treatment.

    In some cases, the bleeding stops, but the placenta blocks the cervix. The mother will need a Cesarean section (C-section) delivery if the placenta completely blocks the cervix. The mother may need a C-section if the placenta only partly blocks the cervix. When this happens, the mother may have more bleeding after she delivers the baby.

    {Note: Some pregnant women may have a “low lying placenta.” This means the placenta lies at the bottom of the uterus (not higher where it should be). An ultrasound can show a “low lying” placenta. If it is found before the 24th week, the placenta can move upward and out of the way of the cervix. If so, there is no longer a problem.}

    Placenta Abruptio

    There is a right time for delivery of the placenta. That’s after the baby is born. But sometimes it happens another way. The placenta starts to leave the wall of the uterus too early. It starts before the baby is born. This can happen whether the placenta is attached high or low.

    Placenta abruptio happens in about 1 in 200 pregnancies. Some cases are more serious than others. Causes might be high blood pressure or a serious blow to the belly. An older mother may be more apt to have placenta abruptio. So are women who use cocaine during pregnancy. Symptoms of placenta abruptio are:

    *  Bright red vaginal bleeding

    *  Severe pain in the abdomen. The pain lasts. It doesn’t come and go.

    There are no tests for placenta abruptio. Even ultrasound may not show it. Regular prenatal visits help. The health care provider looks for blood in the mother’s vagina. The provider finds out if the uterus is tender.

    Women with placenta abruptio need to go to the hospital right away. Some women can have a vaginal delivery. That’s if labor begins on its own and the baby is healthy. Otherwise, a C-section is done. The mother may be given blood.

    Questions to Ask

    Self-Care / Prevention

    *  Watch closely for bleeding. If you see any, call your health care provider.

    *  Rest in bed for light bleeding.

    *  Avoid doing things that could injure you. Examples: heavy lifting, hard exercise. Don’t do work, sports, or exercises that could give you a blow to the belly.

    *  Wear a special seat belt when you drive. You can get one that protects a pregnant woman’s belly.

    *  Don’t smoke.

    *  Don’t be exposed to other people’s smoke.

    *  Follow your health care provider’s advice about sex. You may be told to:

    – Avoid sex.

    – Use extra caution during sex:

    – Your partner can focus on more gentle touching.

    – Limit how deeply the penis enters the vagina. Use positions that help control the depth.

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Bleeding 2

    First Aid

    Most adults can donate a pint of blood without harmful side effects, but losing a quart of blood, quickly, can lead to shock and even death. In a child, losing a pint (or less depending on the child’s size) can put the child in extreme danger.

    Signs & Symptoms

    For External Bleeding

    *  A skin wound.

    *  Dark red blood gushes or flows from veins.

    *  Bright red blood spurts from arteries.

    *  Blood oozes from capillaries. The bleeding usually clots off by itself.

    For Internal Bleeding

    *  Vomiting or coughing up true, red blood. This includes blood-tinged sputum.

    *  A bruise on the skin of the chest or abdomen, especially if it is in a place where no blow was struck.

    *  Fractured ribs.

    *  Dizziness. Fainting. Weakness.

    *  Lethargy. Excessive sleepiness. Mental status changes. These can occur with trauma to the head, even if it is mild.

    *  Fast pulse. Cold, moist skin.

    *  Stools contain bright red blood or are black (not due to taking iron).

    Causes

    For External Bleeding

    *  Abrasions (scraped skin). Lacerations (cut skin with jagged edges). Punctures.

    *  Knife, gunshot, or other wounds can graze or penetrate the skin. These can damage internal blood vessels and body organs.

    *  Injury wounds.

    For Internal Bleeding

    *  A bruise. This is bleeding from and damage to tissues beneath the skin.

    *  Damage to blood vessels and/or internal structures. This includes a blunt injury that does not break the skin, a bleeding ulcer, and an aneurysm.

    *  Bleeding disorders.

    Taking blood-thinning drugs can result in both internal and external bleeding.

    Treatment

    When bleeding occurs, the goal is to find the source, stop or lessen the bleeding, and help the body cope with the loss of blood.

    *  For severe bleeding, treatment includes first aid measures and emergency medical care.

    *  For minor bleeding, treatment depends on the cause and other medical conditions present.

    *  Bleeding disorders need to be treated by a doctor.

    Questions to Ask

    Self-Care / First Aid

    For Severe Bleeding

    *  Without delay, apply direct pressure to the wound using a sterile dressing or clean cloths. {Note: If the cut is large and the edges of it gape open, pinch the edges of the wound while you apply pressure.}

    *  Call 9-1-1 or take the person to nearest hospital emergency department.

    *  Do not remove an object that is stuck in a wound. Pack it in place with padding. Put tape around the padding so it doesn’t move.

    *  If bleeding continues before getting medical help, put extra cloths, etc. on top of existing ones. Keep putting pressure on the wound until bleeding stops or until medical help takes over.

    *  The most important thing to do is to apply direct pressure on the bleeding site. Some health experts advise to do these things, too, if needed:

    – Elevate the wounded area higher than heart level while applying pressure. Do this if no bone is broken.

    – Apply pressure to a “pressure point” if bleeding still continues after 15 to 20 minutes of direct pressure. Use the pressure point closest to the bleeding site that is between the wound and the heart. (See Pressure Points.)

    *  Don’t apply a tourniquet except to save a life.

    *  While giving first aid for bleeding, keep looking for signs of shock.

    For an Amputation

    *  Control bleeding.

    *  Wrap the severed part in a clean, dry (not wet) cloth or sterile gauze. Place the wrapped part in a plastic bag or other waterproof container. Put these on a bed of ice. Do not submerge the severed part in cold water or ice.

    For Bleeding from the Scalp

    *  Use a ring pad to apply pressure around the edges of the wound, not on the wound. Make a ring pad (shaped like a doughnut) with a bandage of narrow, long strips of cloth. Start with one end of the narrow bandage and wrap it around all four fingers on one hand until you form a loop. Leave a long strip of the bandage material to weave in and around the loop so it doesn’t unravel.

    Healthier at Home book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • How Your Body Changes, How Your Baby Grows

    Pregnancy & Prenatal Care

    A full-term pregnancy lasts about 40 weeks. You begin counting from the start of your last menstrual period. That’s about 9 calendar months. The 9 months are divided into 3 parts. Each part is called a trimester. The trimester charts that follow show changes in your body. They show how your baby grows.

    First Trimester

    (Months 1-3, Weeks 1-13)

    Changes in Your Body

    *  Your hormones change.

    *  Your body makes more blood and body fluids.

    *  You may feel very tired.

    *  You pass urine more often.

    *  You may have an upset stomach, or throw up (morning sickness). This can happen any time of the day.

    *  You may feel light-headed or dizzy.

    *  You gain a few pounds. The average is 3 or 4 pounds. Your clothes begin to feel a little tight.

    *  Your moods can vary. You may feel happy and elated. You may also feel sad, cross, or anxious.

    *  Your breasts may change.

    – They may get bigger.

    – They may get sore and tender.

    – Your nipples get darker. They may stick up more.

    How Your Baby Grows

    Your baby starts out as a single cell. The cell is formed when your egg and your male partner’s sperm meet. That one cell divides into many cells. These attach to the wall of your uterus. Some of the cells form the placenta. The rest become the embryo. That’s what the unborn baby is called from week 4 to week 8. After 8 weeks, it is called a fetus. By the end of the first trimester, your baby:

    *  Is about 3 to 4 inches long

    *  Weighs about 1 ounce

    *  Has all its internal organs and limbs. Its heart beats.

    *  Has a large head compared to the rest of its body. Its eyes are closed.

    *  Begins to develop sex organs

    *  Has well-formed fingers and toes. Fingernails and toenails are forming.

    *  Can move in the uterus. You can’t feel that yet, though.

    Second Trimester

    (Months 4-6, Weeks 14-27)

    Changes in Your Body

    *  You probably feel really good during this trimester. Most women do.

    *  You start to look pregnant as your belly expands. You gain about a pound a week. Loose or maternity clothes feel best.

    *  Your heart beats stronger. This helps push the extra body fluids around your body. It helps push them into the placenta, too.

    *  You start to feel your baby move. This usually starts between weeks 15 and 20 with a first baby. It may come earlier than that with babies after the first one. First you feel flutters. Then you feel kicks.

    *  Your breasts get ready to make milk.

    *  Your uterus starts to stretch out and get thinner.

    *  You may notice that you have:

    –  Backache

    –  Constipation

    –  Headache

    –  Mood swings

    –  Braxton-Hicks contractions

    –  Mild swelling of the ankles and feet

    –  Less morning sickness or none at all

    –  Less need to pass urine

    –  Bigger appetite

    –  Heartburn

    –  Larger veins in your hands and arms

    –  Stretch marks on your breasts and belly

    –  Leg cramps at night

    None of these is apt to change your sense of well-being, though.

    How Your Baby Grows

    Your baby begins to grow fast. Its organs mature. By the end of the second trimester, your baby:

    *  Is about 11 to 14 inches long

    *  Weighs about 2 to 2-1/2 pounds

    *  Swallows

    *  Sucks its thumb

    *  Moves and kicks

    *  Has wrinkly skin. Its skin is covered by a thick, white coating called vernix.

    *  Has hair growing on its head

    *  Has teeth forming in the jawbone

    *  Can open and close its eyelids

    *  Has eyes that are almost fully developed. Eyebrows and eyelashes start to grow.

    Third Trimester

    (Months 7-9, Weeks 28-40)

    Changes in Your Body

    You gain about a pound a week until the final few weeks. Then you may stop gaining weight or lose a pound or two. As the baby grows, your uterus and belly expand. You feel lots of pressure on your bladder. You need to pass urine more often.

    The baby pushes up on the bottom of your rib cage. The baby pushes up on the diaphragm. This can cause you to feel short of breath.

    The baby makes stronger movements and moves more often. You can feel its head, elbows, and feet as they push against your belly. You may be able to see the baby’s kicks! You may notice that:

    *  You feel hot and you sweat more than usual.

    *  A yellow liquid leaks from your breasts.

    *  Your hands and feet swell.

    *  Your navel may look flat or stick out.

    *  You feel tired.

    *  You have mood swings.

    Toward the very end of this trimester (near your due date):

    *  You may feel your uterus getting tight and hard.

    *  You may have “practice” contractions. These stop when you move your body or walk around.

    *  The baby “drops” into your pelvis. It is easier for you to breathe. It also makes you need to pass urine more often.

    *  You lose the mucus plug. You usually lose it shortly before delivery. It’s called bloody show then. You may notice it as a thick, stringy discharge for days. Or you may pass a big clump that looks like a wet cotton ball. Some women never notice the bloody show.

    How Your Baby Grows

    Your baby keeps growing and gaining weight. During this trimester, your baby:

    *  Grows to about 20 inches long

    *  Gains weight to 7 pounds or more

    *  Fills the uterus

    *  Opens and closes its eyes

    *  Responds to light and sound

    *  Moves a lot. Its movements are more like rolls and turns instead of kicks. These may slow down close to labor. But the baby does not stop moving before birth. Tell your health care provider if you notice a big decrease in your baby’s activity.

    *  Settles further down into your pelvis. Your baby is getting ready to be born!

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Choosing Your Health Care Provider

    Pregnancy & Prenatal Care

    Read the options below. Discuss them with your health insurance carrier. Do this before you get pregnant. Who you choose will partly depend on:

    *  Your health insurance coverage.

    *  You may need to choose from a certain list. Find out who is on it. Ask if there is a waiting period for maternity coverage.

    *  The health care providers in your area

    Your personal wishes are important, too. For example, do you prefer a female or a male provider? Do you want a provider who works alone? Or do you want one in a group practice?

    Where You Can Give Birth

    Where do you want to have your baby? These are places to think about:

    *  Hospitals. There may also be choices within hospitals. These could be:

    – Regular delivery room. Your family may be able to be with you here.

    – Birthing center or birthing room. Your family can be with you here.

    – Special high-risk pregnancy section. Sometimes mothers and newborns need high-risk care. Some hospitals offer high-risk care. Find out what services local hospitals can offer.

    *  Birthing centers not inside hospitals. These are sometimes called alternative birthing centers. They are for low-risk pregnancies. Find out what hospital is used when special needs arise.

    {Note: Your special needs during pregnancy may determine where you can have your baby. Do not plan a home birth. It is not safe for you and your baby.}

    Types of Providers

    *  OB/GYN (obstetrician/gynecologist). This doctor gives prenatal and delivery care. That care ends 6 weeks after delivery. The OB/GYN treats women when they’re not pregnant, too. You may already have an OB/GYN. If you do, you could choose this provider for your pregnancy. Most women choose an OB/GYN. If you belong to an HMO, you may need a referral for an OB/GYN. A referral is when your primary care provider says you need a special doctor. You don’t need a referral if the OB/GYN is your primary care provider. You also don’t need a referral if your HMO lets you pick an OB/GYN plus a primary care provider.

    *  Family practice doctor. A family practice doctor can act as an OB/GYN, an internist, and a pediatrician. That means the provider can give you prenatal care and deliver your baby. You and your child can both go on seeing this same provider afterward. But if you need a cesarean section (c-section), you will need an OB/GYN.

    *  Maternal and fetal medicine specialist. This provider may be needed to help with high-risk pregnancies. Your primary care doctor or your OB/GYN would give you a referral if he or she can’t provide the care needed for your high-risk problems.

    *  Infertility specialist. This provider helps persons who want to get pregnant, but haven’t been able to after trying for a year. You may want to see this doctor if your regular OB/GYN cannot help you with your needs.

    *  Certified nurse-midwife. This provider cares for women with low-risk pregnancies. The nurse-midwife is trained to handle low-risk births. Be sure he or she works with a medical doctor. A lay midwife cannot provide total care. Find out if your insurance will pay for a nurse-midwife. Be sure the midwife is certified. Call the American Midwifery Certification Board (AMCB) at 866.366.9632 or go to its Web site:www.amcbmidwife.org.

    How to Find a Provider

    There are a lot of ways to find providers who might suit you:

    *  Look in the directory of providers from your health insurance carrier.

    *  Ask your regular doctor or specialist.

    *  Do you have any friends who had a baby recently? Are their ideas about having babies like yours? Ask them.

    *  Call information at the hospital you want. Ask for the name and phone number of the nurse in charge of the maternity section. Ask for the name and phone number of a resident in obstetrics who works at that hospital. A resident is a doctor who is in training. Ask for the “Physician Referral Service.” Call any or all of them and ask what doctor(s) they recommend.

    *  Call the medical school closest to you. Ask which obstetricians it recommends.

    *  Ask your county medical society.

    *  Look in the Directory of the American Medical Association. Ask for this at your doctor’s office or library.

    *  Look in the Directory of Medical Specialties for OB/GYNs. Your doctor’s office or library should have this, too.

    *  Look for a doctor who can take care of special needs you may have.

    *  Do you want a doctor with a high interest in prepared childbirth? Prepared childbirth is a special approach. The pregnant mother goes to classes. Her partner or other childbirth “coach” goes with her. They both learn ways of helping the birth happen, like special breathing. The doctor works with the mother in this approach to childbirth.

    How to Follow Up with a Provider

    Have you found some likely prospects? Now you can:

    *  Call the American Board of Medical Specialties at 866.275.2267 or go to its Web site:www.abms.org. Find out if the provider is properly trained and licensed.

    *  Ask yourself some questions.

    – Do you think you could work well with the provider?

    – Does the provider’s office seem to be managed well?

    *  Ask the provider some questions. You may be able to do this on the phone. (You may be charged an office visit for the phone call.) Or you may need to make a date to meet in person. Here are some questions to ask. You will think of others.

    – Does the provider accept your health insurance? What do services cost? How must payment be made? How much do you have to pay?

    – What hospital(s) does the provider use?

    – Is the hospital accredited? The Joint Commission on Accreditation of Healthcare Organizations (JCAHO) does this.

    – Does the hospital have a birthing center or birthing room?

    – Does it have a Level III neonatal intensive care unit (NICU)?

    – Can fathers and other persons be with you in the delivery room? In the operating room?

    – Will the provider be the one who delivers your baby?

    – Does the provider have partners who share the practice? If so, what would their roles be?

    – Would a resident deliver your baby? A resident is a doctor in training.

    – How would you reach your OB/GYN or health care provider? Would this differ at certain times of day or night? For emergencies?

    – Who would take care of you when your health care provider is away?

    – What is the provider’s Cesarean section (C-section) rate? If the rate is more than 35%, ask why.

    – For what reasons does the provider do a C-section?

    – Does the provider prefer a certain form of pain relief? If so, what and why?

    – At the place you will deliver, can you get anesthetics for an epidural any time of the day or night? An epidural is an anesthesia that can block most of the pain during labor and delivery.

    – What else can be given for pain?

    You can talk to two or more providers. Compare the answers you get. Then you can decide who will give you care and deliver your baby.

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Ectopic Pregnancies

    Pregnancy & Prenatal Care

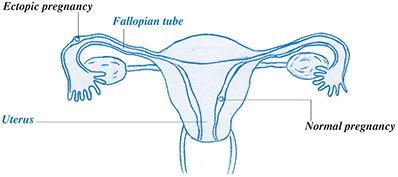
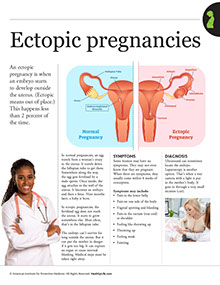
    An ectopic pregnancy is when an embryo starts to develop outside the uterus. (Ectopic means out of place.) This happens less than 2 percent of the time.

    In normal pregnancies, an egg travels from a woman’s ovary to the uterus. It travels down the fallopian tube to get there. Somewhere along the way, the egg gets fertilized by a male sperm. Once inside, the egg attaches to the wall of the uterus. It becomes an embryo and then a fetus. Nine months later, a baby is born.

    In ectopic pregnancies, the fertilized egg does not reach the uterus. It starts to grow somewhere else. Most often, that’s in the fallopian tube.

    The embryo can’t survive for long outside the uterus. But it can put the mother in danger if it gets too big. It can rupture an organ or cause internal bleeding. Medical steps must be taken right away.

    Symptoms

    Some women may have no symptoms. They may not even know that they are pregnant. When there are symptoms, they usually come within 8 weeks of conception. Symptoms may include:

    *  Pain in the lower belly

    *  Pain on one side of the body

    *  Vaginal spotting and bleeding

    *  Pain in the rectum (rear end) or shoulder

    *  Feeling like throwing up

    *  Throwing up

    *  Feeling weak

    *  Fainting

    Diagnosis

    Ultrasound can sometimes locate the embryo. Laparoscopy is another option. That’s when a tiny camera with a light is put in the mother’s body. It goes in through a very small incision (cut).

    Illustration of normal vs ectopic pregnancy.

    Causes

    There are many causes for ectopic pregnancies:

    *  Damage to the ovary or fallopian tube

    *  Scarring of the ovary or fallopian tube. Scarring can result from endometriosis, pelvic inflammatory disease or an STD.

    Also, the risk for an ectopic pregnancy is higher for women who:

    *  Have had an ectopic pregnancy in the past

    *  Have had fallopian tube surgery

    *  Have had problems getting pregnant

    *  Have used an IUD for birth control

    These women should call their health care provider when they miss a menstrual period.

    Treatment

    Medicines may be used. But if some time has passed, surgery may be needed. The embryo is removed. Any damage to the mother’s body is repaired. In some rare cases, a fallopian tube or ovary must be removed. But women have another set of these. So the mother may become pregnant again.

    Questions to Ask

    Self-Care / Prevention

    Tips to Lower the Risk of an Ectopic Pregnancy

    *  Talk to your health care provider about your risks for damage to your fallopian tubes from:

    – STDs

    – Pelvic Inflammatory Disease

    – Endometriosis

    *  Ask if you need to get tested for these and how often. Find out, too, if your health plan pays for these tests.

    *  Schedule any tests needed with your health care provider.

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Gestational Diabetes

    Pregnancy & Prenatal Care

    A pregnant woman can have diabetes. If she didn’t have it before the pregnancy, it’s called gestational diabetes. (Gestational refers to pregnancy.) It can begin any time during pregnancy. It usually begins in the last half, though. It goes away after the baby is born. But the woman has a greater risk of getting diabetes later.

    Symptoms

    *  Feeling very tired

    *  Rapid weight gain

    *  Feeling very thirsty

    *  Having to pass urine often

    Also, a sign for gestational diabetes is when the baby gets too big during the pregnancy.

    All pregnant women should be screened for diabetes. Screening happens through urine and blood tests. Those are part of routine prenatal health care visits.

    Causes

    Any pregnant woman can develop gestational diabetes. But risk factors may be:

    *  Obesity before pregnancy

    *  High blood pressure before pregnancy

    *  Having a baby that weighed more than 9 pounds at birth in the past

    *  Having a stillbirth in the past

    *  Having a child with a birth defect in the past

    *  Being older than 25

    *  Being pregnant with more than one baby

    Treatment

    Special problems can be avoided with treatment. Without treatment, the baby can get too big. The mother may not be able to have a vaginal birth. Other problems are preeclampsia and preterm birth. Preterm birth is when the baby is born 3 or more weeks before the due date. There can also be delivery problems. But a woman with gestational diabetes can have a healthy baby. She needs proper medical care, though.

    Blood sugar must be controlled. This is done through:

    *  Special diet from the health care provider

    *  Exercises from the health care provider

    *  Insulin shots, in some cases, when diet and exercise are not enough. Insulin is a hormone. Among other things, it keeps blood sugar from getting too high. The provider teaches how to do the shots. The provider teaches the mother how to check her own blood sugar. It is important to do what the provider requests.

    *  Having prenatal visits more often. The provider checks the mother’s daily blood sugar record. Tests are done to see how the baby is doing.

    *  Extra care at delivery

    {Note: The baby should be checked for low blood sugar a day or so after birth.}

    Questions to Ask

    Self-Care / Prevention

    If you get diabetes during pregnancy:

    *  Follow the diet and exercise plan your health care provider or dietitian gives you.

    *  Drink at least 8 to 10 cups of fluids a day. Drink enough for your thirst. Limit ones with a lot of sugar. Examples: all kinds of sodas, fruit drinks and juices.

    *  Get plenty of rest when you feel tired.

    *  If you are told to do so, test your blood sugar levels at home. Your health care provider will tell you how. Keep a daily record of the results.

    *  After you have your baby, get your blood sugar checked when your doctor tells you to.

    {Note: Some pregnant women need to give themselves insulin shots at home. If your provider says you need to, you will be shown how. Be sure to give the insulin correctly. It’s an important way of taking care of yourself and your baby.}

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • Getting Ready For Childbirth

    Pregnancy & Prenatal Care

    What to Do First

    *  Choose where you want to have your baby.

    *  Choose a health care provider.

    How to Get Ready

    *  Read books on pregnancy and childbirth.

    *  Take a childbirth class, if you can.

    *  Get regular prenatal care from your health care provider.

    Childbirth Classes Do These Things

    *  Tell you what happens when you give birth

    *  Show you and your partner (or other “coach”) what to do during labor and delivery

    *  Help lessen the fear of giving birth

    *  Help explain what happens with a Cesarean section (C-section). Knowing what to expect is helpful when a C-section is planned. It is helpful, too, if it is not planned, but needs to be done for the safety of you and your baby.

    *  Teach you how to work with the natural birthing process. You can do this through:

    – Exercises that make the muscles used in childbirth stronger

    – Massage

    – Focusing the mind

    – Relaxing and breathing methods

    You can find out about childbirth classes from:

    *  Your health care provider

    *  The maternity department of local hospitals

    *  Local education programs

    *  Local March of Dimes

    Prenatal Self-Care book by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine

  • High Blood Pressure

    Heart & Circulation Problems

    The medical name for high blood pressure is hypertension (hy-puhr-TEHN-shun). High blood pressure (HBP) is when blood moves through the arteries at a higher pressure than normal. The heart strains to pump blood through the arteries.

    Signs & Symptoms

    High blood pressure (HBP) is a “silent disease.” Often there are no signs or symptoms. A lot of adults with HBP do not know they have it. So, get your blood pressure checked at each doctor’s office visit, at least every 2 years, or as often as your doctor advises. When blood pressure is 180 or higher (top number) or 120 or higher (bottom number), these signs of a hypertensive crisis may occur:

    *  Severe chest pain

    *  Severe headache with confusion and blurred vision

    *  Severe anxiety

    *  Shortness of breath

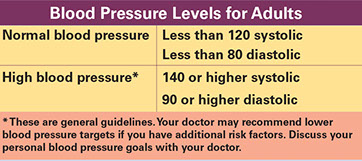
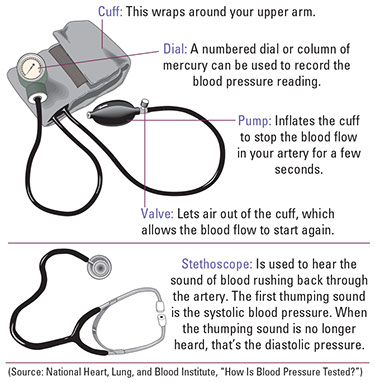
    Blood pressure is measured with 2 numbers. The first (top) number measures systolic pressure. This is the maximum pressure against the artery walls while the heart is pumping blood. The second (bottom) number measures diastolic pressure. This is the pressure between heartbeats when the heart refills. The results are given as systolic over diastolic pressure, such as 120/80 millimeters of mercury (mm Hg).

    Tips When You Have Your BP Measured

    *  Don’t drink coffee or smoke 30 minutes before having your BP read. (Don’t smoke at all!)

    *  Go to the bathroom before you get it checked.

    *  Before the test, sit for 5 minutes.

    *  Wear short sleeves so your arm is exposed.

    *  When you get tested: Sit; keep your back and arm supported; and keep your arm at heart level.

    *  An average of 2 readings from BP tests taken at least 5 minutes apart should be done.

    Causes, Risk Factors & Care

    The exact cause is not known.

    Risk factors include:

    *  Family history of HBP

    *  Aging. More than half of older adults have HBP.

    *  Smoking cigarettes

    *  Race. African Americans are more likely to have HBP than Caucasians.

    *  Gender. Men are more likely to have HBP than women (until women reach menopause).

    *  Being inactive. Obesity. Sleep apnea.

    *  Drinking too much alcohol

    *  Too much sodium intake in some persons

    *  Emotional distress

    High blood pressure could be caused by another medical problem or be a side effect of some medicines. This is called secondary hypertension. This can usually be reversed when the problem is treated.

    Diagnosis

    Blood pressure readings tell if your blood pressure is high. A health care professional measures blood pressure during an office visit with a manual or automated device called a sphygmomanometer (sfig’-mo-ma-nom-e-ter). The numbers on the gauge measure your blood pressure in millimeters of mercury (mm Hg).

    You should get 2 or more readings at different times. To confirm a diagnosis of HBP, your doctor may have you wear a device that records your blood pressure every 20-30 minutes over a period of 24 to 48 hours. This is called ambulatory blood pressure monitoring (ABPM).

    Note: Sometimes just being at the doctor’s office is enough to raise some people’s blood pressure. This is called “white-coat hypertension.” If you think this affects you, tell your doctor. You may be advised to check your blood pressure with a home testing device. Your doctor may have you wear a device that records your blood pressure for 24 hours. This will give accurate readings of your blood pressure.

    Health Problems Related to HBP

    High blood pressure plays a major role in these health problems:

    *  Stroke. Dementia. Brain damage.

    *  Heart disease. A person with HBP is 5 times more likely to have a heart attack than a person without HBP. It can also cause the heart to enlarge. This could cause (congestive) heart failure.

    *  Chronic kidney disease

    *  Kidney failure

    *  Vision loss. This includes blindness.

    Why is ambulatory blood pressure monitoring (ABPM) done?

    During an office visit, a short-term rise in blood pressure can be due to:

    *  Emotions or stress

    *  Pain or physical activity

    *  Caffeine or nicotine

    *  “White-coat hypertension.” With this, just being at a doctor’s office or in the presence of medical staff is enough to raise blood pressure.

    Getting blood pressure readings over 1-2 days during normal activity and sleep gives a more accurate measurement of your blood pressure.

    Self-Care / Prevention

    For blood pressure control, follow a healthy lifestyle.

    *  Get your blood pressure checked at each office visit, at least every 2 years, or as often as your doctor advises.

    *  Get to and/or stay at a healthy weight. Aim for a body mass index (BMI) between 18.5 and 24.9. Find your BMI using the table below or from:www.nhlbisupport.com/bmi.

    *  Don’t smoke. If you smoke, quit.

    *  Limit alcohol to 2 drinks or less a day if you are male and 1 drink or less a day if you are female or age 65 or older.

    *  Limit caffeine.

    *  Exercise. Try to do at least 60 minutes a day.

    *  Learn to handle stress. Take classes. Learn relaxation techniques, etc.

    *  Take medicine as prescribed. Tell your doctor if you have any side effects, such as dizziness, faintness, or a dry cough without having a cold. Don’t stop taking your prescribed medicine or change the dose(s) unless your doctor tells you to.

    *  Talk to your doctor or pharmacist before you take antihistamines and decongestants. Discuss all prescribed and over-the-counter medicines with your doctor and pharmacist before you take them to avoid harmful drug interactions. Find out about drug and food interactions, too. Ask if grapefruit juice can cause harmful effects with the medicine(s) you take.

    *  Keep track of your blood pressure using a home testing device. Do this if advised by your doctor.

    Medical Care

    High blood pressure usually lasts a lifetime, but can be treated and controlled. If you are diagnosed with high blood pressure, follow your doctor’s advice. Medical treatment includes:

    *  A physical exam and lab tests. These check for damage to your heart, kidneys, and other organs. They also identify risk factors you have for heart, kidney, and other diseases. Your treatment plan is based on your needs.

    *  Follow-up blood pressure checks and other tests as needed.

    *  Healthy lifestyle changes.

    *  Medications. Most persons need more than 1 medicine to treat high blood pressure.

    Your doctor will decide if and what medication(s) you need. This is based on your blood pressure level, age, race, other conditions you have, heart disease risk factors, etc. Common medicines used to treat HBP are:

    *  Diuretics (water pills)

    *  Calcium channel blockers

    *  ACE inhibitors

    *  Angiotensin II receptor blockers

    *  Beta-blockers

    *  Alpha blockers. Alpha-beta blockers.

    *  Nervous system inhibitors

    *  Vasodilators

    Reasons to Get Medical Care

    *  You have signs or symptoms of a hypertensive crisis. Get medical care right away.

    *  You need to schedule office visit appointments to get your blood pressure checked. Do this as often as your doctor advises.

    *  You have adverse side effects from taking medicine(s) to lower blood pressure. Examples are:

    – You feel lightheaded or dizzy.

    – You feel weak, sleepy, and/or drowsy.

    – Your heart races.

    – You get a skin rash.

    Resources

    American Heart Association

    800.242.8721

    www.heart.org

    National Heart, Lung, and Blood Institute

    www.nhlbi.nih.gov

    High Blood Pressure brochure by the American Institute for Preventive Medicine. www.HealthyLife.com. All rights reserved.

    © American Institute for Preventive Medicine